Multiple daily injections (MDI): what they are, how they work, and what to expect
Multiple daily injections (MDI) is an insulin therapy approach that uses two types of insulin to manage glucose throughout the day: a long-acting basal insulin that provides steady background coverage, and a rapid-acting insulin taken before meals and to correct high glucose. For most people, MDI means several injections per day. It's one of the most widely used insulin regimens for people with type 1 diabetes and is also used in type 2 diabetes when insulin is needed throughout the day.

What are multiple daily injections?
Unlike an insulin pump or automated insulin delivery system, MDI is entirely self-administered. You manage insulin delivery yourself by calculating doses, deciding when insulin is needed, and administering injections with an insulin pen or syringe based on guidance by your healthcare provider. Every basal dose and every bolus is a decision you make. Together, they're designed to more closely mirror the way a healthy pancreas releases insulin: steadily in the background, and in response to meals.
MDI is a standard basal-bolus approach in clinical guidelines for people with type 1 diabetes, and it's also used in type 2 diabetes when a single basal dose isn't enough to cover daily insulin needs.¹
The two types of insulin used in MDI
MDI relies on two kinds of insulin working together:
- Long-acting (basal) insulin is injected once or twice a day. It releases slowly over 12 to 24 hours or more, providing a steady background level of insulin between meals and overnight. Basal insulin handles the glucose your liver produces when you're not eating.
- Rapid-acting (bolus) insulin is injected before meals. It works more quickly to match the glucose rise from carbs you eat. It can also be given as a correction dose when your glucose runs higher than your target.
This two-insulin approach is designed to give more flexibility and more physiologically accurate coverage than older fixed-dose regimens.
How many injections a day does MDI involve?
For most people, MDI means several injections per day; long-acting insulin usually taken at nighttime, and rapid acting insulin at mealtimes and any correction doses needed throughout the day. Your healthcare team will help determine how often and when to take each type of insulin. In addition to injections, people on MDI either use a CGM or they may check their glucose several times a day using a blood glucose meter to guide their dosing decisions. The exact number of injections varies by person and care plan, and your healthcare provider will work with you to determine what's right for your situation.
The benefits of MDI therapy
MDI is a widely used approach to insulin therapy that allows people to adjust insulin doses for meals, glucose levels, and daily activities as part of their diabetes management plan. Here's what makes it work well for so many people.
No wearable device required
MDI doesn't require wearing a device to dose insulin. For people who prefer not to have a device on their body (whether for personal comfort, work environment, or lifestyle), that can be an advantage.
Widely available and familiar to most endocrinologists
MDI uses insulin products and delivery tools (pens, cartridges, and syringes) that are familiar to nearly every diabetes care team in nearly any clinical setting. If you're newly diagnosed, your healthcare team may offer MDI as the first approach.
Ability to make correction doses with rapid-acting insulin
With MDI, you can take an additional dose of rapid-acting insulin any time your glucose runs higher than your target. That flexibility to correct on demand is a meaningful step up from older insulin regimens that offer less flexibility between meals.
The limitations of MDI
MDI works well for many people and at the same time asks a lot of you every single day. Below are limitations that people who have been on MDI for months or years can often feel accumulate over time.
Needle fatigue and injection frequency
Multiple daily injections add up quickly. If someone takes four injections per day, that's about 120 injections in a month and more than 1,400 in a year. Even with modern ultra-fine pen needles, the physical and psychological weight of that repetition can build over time. Injection burden and needle fatigue are well-recognized challenges in long-term MDI management, and they're among the primary reasons people eventually explore alternatives.¹
The mental load of MDI
Managing MDI means making active dosing decisions at nearly every meal: estimating how many carbs you're eating, calculating the right bolus, timing the injection to align with how quickly a particular food will raise your glucose, and adjusting for exercise, stress, or illness. That cognitive overhead is part of every day, not just when something goes wrong. Research shows that more than half of adults with diabetes in the U.S. experience some form of diabetes burnout, and the daily demands of dosing decisions could be a meaningful contributor.²
Overnight control and long-acting insulin variability
One of MDI's structural limitations is overnight glucose control. A long-acting basal insulin is designed to provide steady background insulin coverage while you sleep, but the dose is set ahead of time and cannot automatically respond to changing glucose levels overnight. Insulin absorption can vary depending on factors such as the injection site.³ That variability could make it harder to reliably stay in your target glucose range from bedtime to morning without additional adjustments.
Who is MDI right for?
The right insulin regimen depends on where you are in your diabetes journey, what matters most to you in daily management, and how your glucose patterns look on your current approach.
Signs MDI is the right fit
MDI tends to work well if you:
- Prefer not to wear a device on your body
- Are newly diagnosed and still building confidence with insulin management
- Have glucose patterns that a basal/bolus regimen can cover consistently
- Are comfortable with decisions about dosing and timing that MDI requires
Signs it's worth exploring MDI alternatives
MDI may start to feel limiting, and alternatives may be worth a conversation with your healthcare professional, if you:
- Find the daily mental load of meal planning and dose timing exhausting over time
- Struggle with overnight glucose patterns that's hard to manage with a fixed basal dose
- Notice needle fatigue building after months or years of multiple daily injections
- Want more schedule flexibility without as much real-time calculation
- Find that your current regimen isn't getting your glucose where you and your healthcare provider want it to be
MDI vs. insulin pump therapy: a practical comparison
If you're weighing MDI against insulin pump therapy, the comparison often comes down to a few practical questions: How much physical and mental overhead is manageable for you? How important is overnight control? And how do you feel about wearing a device?
The table below lays out how the two approaches compare across the dimensions that tend to matter most.
| MDI | Insulin pump therapy (includes HCL and non-automated insulin pumps) | |
| Physical delivery | Several injections per day | Continuous delivery; device site changes every few days |
| Basal insulin | One or two long-acting injections daily | Rapid-acting insulin delivered continuously at programmable rates; adjusted based on sensor values if on HCL system |
| Overnight control | Fixed long-acting dose; hard to target specific overnight patterns | Adjustable overnight basal rates; automated systems respond to real-time glucose changes |
| Device requirement | No on-body device to deliver insulin | Worn continuously, whether it's tubeless patch/Pod pump or tubed insulin pump |
| Lifestyle flexibility | No device to wear for dosing insulin | No multiple daily injections; all insulin is delivered through the pump |
| Learning curve | Familiar to most care teams; may be learning curve for patients | Initial training with a healthcare provider required; most people adapt within a few weeks |
The day-to-day difference between MDI and insulin pumps
In practice, one of the biggest day-to-day differences between MDI and insulin pump therapy is how insulin delivery is managed. With MDI, you typically take long-acting insulin once or twice a day and calculate mealtime and correction doses as needed. Depending on the pump system, insulin delivery can be adjusted throughout the day, and automated insulin delivery (AID) systems can automatically respond to glucose changes. For many people, this can reduce some of the day-to-day decision-making and manual adjustments involved in managing diabetes. The full range of insulin pump benefits goes beyond daily convenience and is worth discussing with your healthcare provider.
For people who use an automated insulin delivery (AID, or Hybrid Closed Loop ]system, a pump works together with a continuous glucose sensor and a dosing algorithm to automatically adjust insulin delivery. The system responds to glucose changes between meals and overnight without manual input from you.
What makes Omnipod® different from tubed pumps
Some people hesitate to try insulin pump therapy because of concerns about the physical aspects of wearing a device, including the tubing that connects traditional pumps to the infusion site on the body.4 If you've ever tried a conventional pump and found the tubing limiting or uncomfortable, that hesitation makes sense.
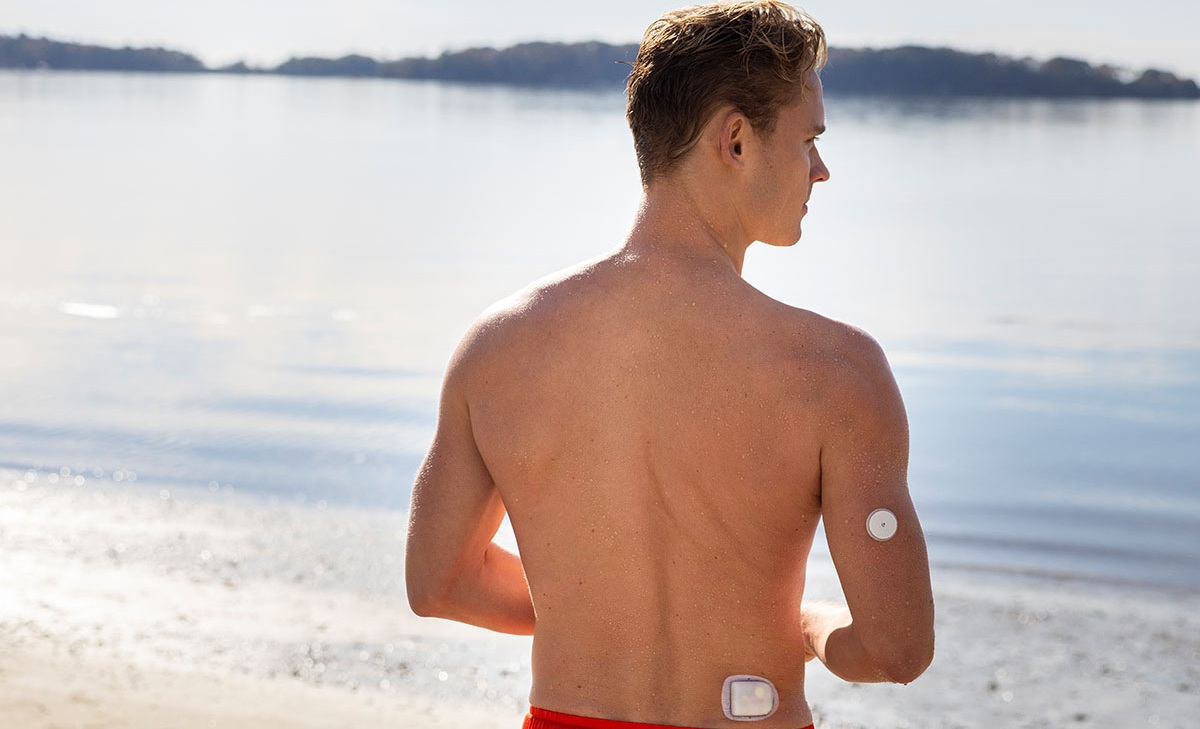
Rather than connecting to a reservoir through tubing, the Omnipod® 5 Automated Insulin Delivery System involves a small, wearable Pod that attaches directly to your skin and delivers insulin wirelessly. It pairs with compatible sensors* to automatically adjust insulin delivery.


Related Articles


Other topics
References and Disclaimers
*For a list of compatible sensors, please visit omnipod.com/sensorintegrations
1. Brixner D, Edelman SV, Sieradzan R, Gavin JR III. Diabetes Therapy (2024). Narrative review of clinical and economic impacts of suboptimal glycemic control in adults with type 2 diabetes on basal-bolus insulin (MDI), and barriers to optimal MDI utilization, including injection pain, needle aversion, supply management demands, and social stigma as recognized drivers of suboptimal dosing. Diabetes Ther 15(7):1525-1534. DOI: 10.1007/s13300-024-01598-3.
2. Alexander DS, Saelee R, Rodriguez B, Koyama AK, Cheng YJ, Tang S, Rutkowski RE, McKeever Bullard K. Preventing Chronic Disease (2025). Cross-sectional study of 2021 National Health Interview Survey data among U.S. adults with diagnosed diabetes examining prevalence of diabetes distress. Adjusted prevalence of moderate and severe diabetes distress: 24.3% (95% CI, 22.5%–26.1%) and 6.6% (95% CI, 5.6%–7.8%), respectively; overall, more than half of U.S. adults with diabetes experienced diabetes distress. PMC11870017.
3. American Diabetes Association Professional Practice Committee for Diabetes. 9. Pharmacologic Approaches to Glycemic Treatment: Standards of Care in Diabetes—2026. Diabetes Care 2026;49(Suppl. 1):S183-S215.
4. Pauley ME, Berget C, Messer L, Forlenza G. Barriers to Uptake of Insulin Technologies and Novel Solutions. Medical Devices: Evidence and Research 2021;Volume 14:339-354. doi:10.2147/mder.s312858
The information provided is not intended as a substitute for professional medical advice. Individual symptoms, situations, and circumstances may vary. Please consult your Healthcare Professional regarding your condition and appropriate medical treatment.
The Omnipod 5 Automated Insulin Delivery System is a single hormone insulin delivery system intended to deliver U-100 insulin subcutaneously for the management of type 1 diabetes in persons aged 2 and older requiring insulin.
The Omnipod 5 System is intended to operate as an automated insulin delivery system when used with compatible Continuous Glucose Monitors (CGM). When in automated mode, the Omnipod 5 system isdesigned to assist people with type 1 diabetes in achieving glycaemic targets set by their healthcare providers. It is intended to modulate (increase, decrease or pause) insulin delivery to operate within predefined threshold values using current and predicted CGM values to maintain blood glucose at variable target glucose levels, thereby reducing glucose variability. This reduction in variability is intended to lead to a reduction in the frequency, severity, and duration of both hyperglycaemia and hypoglycaemia.
The Omnipod 5 System can also operate in a manual mode that delivers insulin at set or manually adjusted rates.
Warning: DO NOT start to use the Omnipod® 5 System or change settings without adequate training and guidance from a healthcare provider. Initiating and adjusting settings incorrectly can result in over-delivery or under-delivery of insulin, which could lead to hypoglycaemia or hyperglycaemia.