What is an automated insulin delivery (AID) system?
An automated insulin delivery (AID) system is a three-part technology that combines a wearable sensor, an insulin pump, and an algorithm to automatically adjust your insulin delivery based on real-time glucose readings. It's one of the most significant advances in diabetes management in decades, and for many people with diabetes, it means less manual decision-making and more time with glucose in their target range.
Unlike a traditional insulin pump, an AID system reads your glucose levels continuously and adjusts insulin delivery automatically.
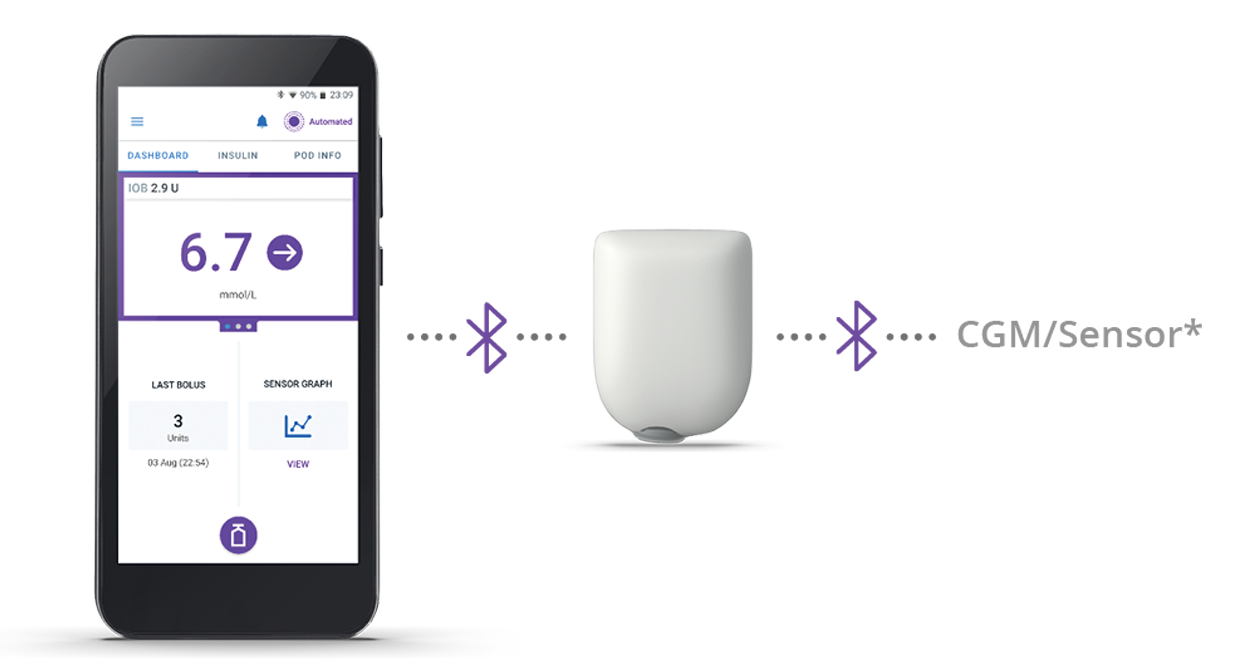
How does an automated insulin delivery system work?
An AID system has three core components that work together continuously: a sensor that monitors your glucose levels, an insulin pump that delivers insulin, and a software algorithm. The sensor sends glucose readings to the algorithm every few minutes. The algorithm uses those readings to decide how much insulin the pump should deliver, making small automatic adjustments throughout the day and night. Here's how each component works.
Continuous glucose monitor (CGM)
A sensor, often called a continuous glucose monitor (CGM), is a wearable device you place on your arm, abdomen, or another approved body site with an adhesive patch. It measures glucose in the interstitial fluid (the fluid between your cells) and sends the values to the AID system every few minutes. The sensor values and their trend arrows give a real-time picture of where your glucose level is currently and where it’s headed.
Insulin pump
An insulin pump is a small device that delivers insulin directly into the body, replacing the multiple daily injections (MDI) approach of using a syringe or pen to inject insulin several times a day. A pump can deliver insulin in two ways:
- Basal insulin: A small, steady background rate of insulin delivered continuously throughout the day and night to manage glucose between meals.
- Bolus insulin: A larger dose delivered when you eat or need to correct a high glucose level.
Not all insulin pumps are AID systems. A traditional pump delivers insulin based on programmed basal rates; an AID system pairs a pump with a sensor and algorithm, giving it the ability to adjust insulin automatically.
Insulin pump technology
The algorithm ties the system together. It receives sensor values, predicts where your glucose is heading, and adjusts insulin delivery automatically, increasing it when glucose is rising and decreasing or pausing it when glucose is falling.
Each AID manufacturer uses its own algorithm, which is one reason systems can behave differently from one another even when used with similar sensors.
Automated insulin delivery in practice
How the AID algorithm works
Most AID systems update their insulin delivery decisions every few minutes. AID systems can make decisions about insulin delivery by looking at several factors, including sensor glucose values, glucose trends, and insulin on board (IOB) which is the amount of insulin still active in your body from recent doses.
Based on that data, the algorithm adjusts your insulin delivery up, down, or pauses it temporarily. If your glucose is heading high, the system delivers more insulin. If it's dropping toward the low glucose range, it slows or pauses delivery to help minimize lows.1
AID systems are often called "hybrid closed-loop" systems because while they automate basal insulin delivery, they still require you to interact with the system; for example, you need to manually bolus for meals. You enter how many carbs you're eating, and the algorithm calculates and delivers the appropriate dose. Some AID algorithms are able to adapt and refine over time to changing insulin needs.
Real-life scenarios
Here's how AID systems respond to common situations:
- Exercise: Not all exercise affects glucose levels the same way. Depending on the type, intensity, and duration of the activity, your glucose levels may decrease, increase, or fluctuate during and after exercise. An AID algorithm that detects a falling trend during exercise will automatically reduce or pause basal delivery to help prevent low glucose. Some systems also include an exercise feature you can activate before you start.
- Meals: All hybrid closed-loop AID systems still require you to bolus for meals. The algorithm handles basal insulin needs, but you tell the system what you're eating. Accurate carb counting helps the system calculate a more precise dose.
- Travel: When traveling with diabetes, the algorithm adjusts to your actual glucose data, which can help smooth out the disruptions that come with crossing time zones or changing your routine.
- Overnight: AID systems work while you sleep, making continuous adjustments through the night to help keep your glucose in range.
Benefits of automated insulin delivery systems
Lifestyle benefits
Managing insulin, glucose levels, and daily decisions around food and activity is demanding. Over time, many people with diabetes experience what clinicians call diabetes burnout: a state of emotional exhaustion from the constant demands of managing the condition. AID systems are designed to take some of that mental load off your plate. Potential benefits may include improvement in A1C levels and time in range, as well as other psychosocial benefits.1

Clinical benefits
AID systems are designed to help reduce time spent outside your target glucose range. Spending more time in range is linked to lower A1C levels and reduced risk of complications.1,2
AID adoption has grown significantly as systems have become more accessible for people with diabetes.
What to look for in an AID system
Not all AID systems work the same way. Here are the key differences to understand when researching your options and talking with your care team.
Tubeless vs. tubed design
Traditional insulin pumps are tubed. A small insulin reservoir within the pump itself connects via thin plastic tubing to a cannula, which is a tiny soft tip inserted under the skin. The pump is worn in a pocket or clipped to clothing, and the insulin from the reservoir flows through the tubing into the body at the insertion site.
A tubeless insulin pump uses a self-contained wearable unit (called a Pod in some systems) that adheres directly to your skin. The insulin reservoir, pump mechanism, and cannula are all integrated into a single device, with no external tubes. These devices can typically be worn on a range of body sites, making it easier to sleep, swim*, exercise, and wear a wider variety of clothing without managing tubing. For many people, the absence of tubes is a meaningful quality-of-life difference. Pod therapy is one approach to tubeless insulin delivery that uses a small adhesive device worn on the body.
Algorithm approach
AID algorithms differ in how far ahead they look, most commonly 30 minutes or one hour. Predictive algorithms can use your glucose level and trend data to anticipate where your glucose is going and adjust insulin delivery proactively, before a high or low develops. Ask your care team how a given system's algorithm makes its dosing decisions, and whether it adapts to your individual patterns over time.
Sensor compatibility
Each AID system works with specific sensors. Some systems may be compatible with one sensor model; others integrate with several options. Sensor choice affects warm-up time, wear duration, and how the algorithm interprets your glucose trends. Ask your healthcare provider which sensors a given AID system supports and whether your insurance covers those sensors.
Age and indication
Not all AID systems are approved for the same people. Some are approved for children as young as two; others are for adults only. Some are approved for people with type 1 diabetes only; others also cover type 2 diabetes. Knowing the age and indication requirements for each system helps narrow your options before your care team discussion.
AID vs. multiple daily injections
For people currently managing diabetes with multiple daily injections (MDI), a long-acting insulin taken once or twice daily and a rapid-acting insulin before meals, here's how hybrid closed-loop AID compares across key factors:
| AID System | Multiple daily injections (MDI) | |
| Insulin delivery | Continuous, automatic insulin adjustments + manual meal boluses | Manual injections for both basal and meal insulin |
| Glucose monitoring | Continuous, via a wearable sensor | Typically via fingerstick† or a sensor |
| Devices worn | Sensor + pump (Pod or traditional device), worn continuously | No wearable device required |
| Algorithm-driven dosing | Yes, adjusts every few minutes | No |
| Meal bolusing | Required | Required |
If you're weighing injections against pump therapy, talking with your healthcare provider about your management patterns, lifestyle, and goals is the best way to decide whether AID is the right next step.
Who is AID right for?
AID systems aren't one-size-fits-all, but many people with diabetes are good candidates. Here's what to consider.
Type 1 diabetes
AID systems were first developed for people with type 1 diabetes, an autoimmune condition where the body makes no insulin. People with type 1 diabetes require insulin around the clock, which makes continuous automated delivery a natural fit. Most AID systems are approved across a wide age range for people with type 1 diabetes.
Age eligibility
Age requirements vary by system. Some AID systems are approved for children as young as two; others are for adults only. If you're a parent researching options for a child or teenager with diabetes, or a caregiver helping someone manage diabetes, ask your endocrinologist or diabetes care team about age-appropriate systems.
What to discuss with your care team
Your healthcare provider can help you evaluate:
- Your comfort level with wearable device technology
- Your current glucose management patterns and where AID may help most
- Your age and diabetes type, and which systems you're eligible for
Considerations before getting started with an AID system
AID systems offer real benefits, but there are considerations worth understanding before you commit.
You'll wear two devices
An AID system means wearing both a sensor and a pump device continuously. Sensor wear schedules vary (most are replaced every seven to 15 days depending on the sensor model). Depending on the system, some components may need to be changed, recharged, or otherwise maintained on a regular schedule.
There's a learning curve
Setting up an AID system includes training with your care team before you get started. What that process looks like varies by system and person, so your care team is the right starting point for understanding what to expect.
Alert and alarm fatigue is real
Sensors generate alerts for high glucose, low glucose, missed readings, and other situations. For some people, managing the volume of alerts, especially overnight, takes adjustment. Working with your care team to fine-tune alert thresholds can help reduce unnecessary interruptions.
You still make some decisions
Hybrid closed-loop systems automate basal insulin management but still require you to bolus for meals and count carbs. AID handles one significant part of diabetes management automatically, but it doesn't replace the whole picture. You'll still need to enter carbohydrate amounts so the system can determine the bolus dose.
Cost and coverage
AID systems require a pump device, a compatible sensor, and ongoing supplies. Coverage varies by public and private coverage.
Omnipod® 5 Automated Insulin Delivery System
The Omnipod 5 Automated Insulin Delivery System is the first and only tubeless AID system in Canada. Its algorithm automatically adjusts insulin delivery every five minutes based on your current and predicted sensor glucose values. Users must still bolus for meals.
It integrates with a range of compatible sensors, giving you flexibility in how you monitor your glucose. Each Pod delivers up to three days of continuous insulin before it's replaced, and with no tubing, you can wear it while swimming.* The system is available as an app on compatible smartphones or via a dedicated Controller.

The system has been shown to help users protect against highs and lows, day and night.3-5
It's indicated for people with type 1 diabetes, ages two years and older.
Learn more about Omnipod 5 or explore Omnipod 5 sensor integrations.
Frequently asked questions about automated insulin delivery
Is automated insulin delivery right for type 1?
Is an AID system the same as a hybrid closed-loop system?
How does AID help with overnight glucose management?
How does AID handle exercise and physical activity?
How do I know if an AID system is right for me?

Related Articles



Other topics
References and Disclaimers
*The Pod has a waterproof IP28 rating for up to 7.6 metres for 60 minutes. The Controller is not waterproof.
†Fingersticks required for diabetes treatment decisions if symptoms or expectations do not match readings.
1. American Diabetes Association. Standards of Care in Diabetes, 2026, Section 7: Diabetes Technology. Recommendations 7.3b and 7.25a. Diabetes Care, Vol. 49, Supplement 1. diabetesjournals.org/care
2. American Diabetes Association. Standards of Care in Diabetes, 2026, Section 6: Glycemic Goals, Hypoglycemia, and Hyperglycemic Crises. Diabetes Care, Vol. 49, Supplement 1. diabetesjournals.org/care
3. Brown et al. Diabetes Care (2021). Study in 240 people with T1D aged 6 - 70 years involving 2 weeks standard diabetes therapy followed by 3 months Omnipod 5 use in Automated Mode. Average overnight time (12AM-6AM) with high glucose in adults/adolescents and children for standard therapy vs Omnipod 5 = 32.1% vs. 20.7%; 42.2% vs. 20.7%. Average day time (6AM-12AM) with high glucose in adults/adolescents and children for standard therapy vs Omnipod 5 = 32.6% vs. 26.1%; 46.4% vs. 33.4%. Average overnight time (12AM-6AM) with low glucose in adults/adolescents and children for standard therapy vs Omnipod 5 = 3.6% vs. 1.2%; 2.5% vs. 1.2%. Average day time (6AM-12AM) with low glucose in adults/adolescents and children for standard therapy vs Omnipod 5 = 2.6% vs. 1.4%; 2.1% vs. 2.0%.
4. Sherr J, et al. Diabetes Care (2022). Study in 80 children with T1D aged 2 to 5.9 years involving 2 weeks standard diabetes therapy followed by 3 months Omnipod 5 use in Automated Mode. Average overnight time (12AM-6AM) with high glucose in children for standard therapy vs Omnipod 5 = 38.4% vs. 16.9%. Average day time (6AM-12AM) with high glucose in children for standard therapy vs Omnipod 5 = 39.7% vs. 33.7%. Average overnight time (12AM-6AM) with low glucose in children for standard therapy vs Omnipod 5 = 3.4% vs. 2.1%. Average day time (6AM-12AM) with low glucose in children for standard therapy vs Omnipod 5 = 3.4% vs. 2.6%.
5. Pasquel FJ, et al. JAMA Network Open (2025). Prospective pivotal trial in 305 participants with T2D aged 18-75 yrs. Study included a 14-day standard therapy (ST) phase followed by a 13-week Omnipod 5 hybrid closed-loop phase. Mean overnight time >180 mg/dL (12AM-6AM) as measured by CGM: ST = 50%, 3-mo Omnipod 5 = 30%. Mean daytime >180 mg/dL (6AM-12AM) as measured by CGM: ST = 55%, 3-mo Omnipod 5 = 36%. Mean overnight time in <70 mg/dL (12AM-6AM) as measured by CGM: ST = 0.10%, 3-mo Omnipod 5 = 0.22%. Mean daytime <70 mg/dL (6AM-12AM) as measured by CGM: ST = 0.16%, 3-mo Omnipod 5 = 0.17%. Statistical testing not done to assess significance of change between ST phase and Omnipod 5 System phase.